
Behavioral therapy is one of the four pillars of obesity treatment. Similar to pharmacotherapy, there are distinct techniques that need to be differentiated. On the ABOM exam, two topics will likely show up frequently: cognitive behavioral therapy and motivational interviewing. Cognitive behavioral therapy tends to be the answer we associate as the treatment of choice for most psychiatric conditions. It helps with depression, anxiety, and many disordered eating conditions, including binge eating disorder. In contrast, for most of us, motivational interviewing is a black hole of seemingly overlapping techniques that utilize many tools with many acronyms. At least, this is how I felt when I started studying these topics. In this blog, I will dive into the different components of each and when each is appropriate to use in practice, hopefully removing some of the confusion.
Let’s look at a sample question that we will use as an example to help differentiate the differences between these two entities.
A 38-year-old woman presents to an obesity medicine clinic requesting pharmacotherapy for weight loss. She reports gaining 30 pounds over the past year and is interested in starting a once-weekly injectable medication, stating her friend has had great success with it. You administer a validated screening tool for disordered eating, which indicates moderate binge eating disorder (BED). These results are addressed with the patient, and you recommend addressing the BED prior to initiating anti-obesity medication, but the patient becomes frustrated, saying, “I just want the medication—why can’t we start that today?” Which of the following is the most effective next step to support long-term success in weight management?
A. Prescribe a GLP-1 receptor agonist and readdress BED in the future
B. Reiterate that treatment for BED must come before any anti-obesity medication
C. Schedule cognitive behavioral therapy sessions
D. Initiate motivational interviewing
E. Refer her to a psychiatrist for evaluation of an underlying mood disorder
Note: Further discussion and explanation of this question can be found at the Facebook group Obesity Medicine Boards Prep- 2026.
Although this patient meets the criteria for moderate BED, and cognitive behavioral therapy (CBT) is the first-line treatment, she does not yet appear to recognize how her eating patterns may be contributing to her weight concerns. To help the patient gain insight and “buy in” to the importance of addressing BED, motivational interviewing (MI) can be a valuable tool. MI is an evidence-based communication approach designed to explore and resolve ambivalence, strengthen intrinsic motivation, and support behavior change, making it particularly well-suited for this scenario.
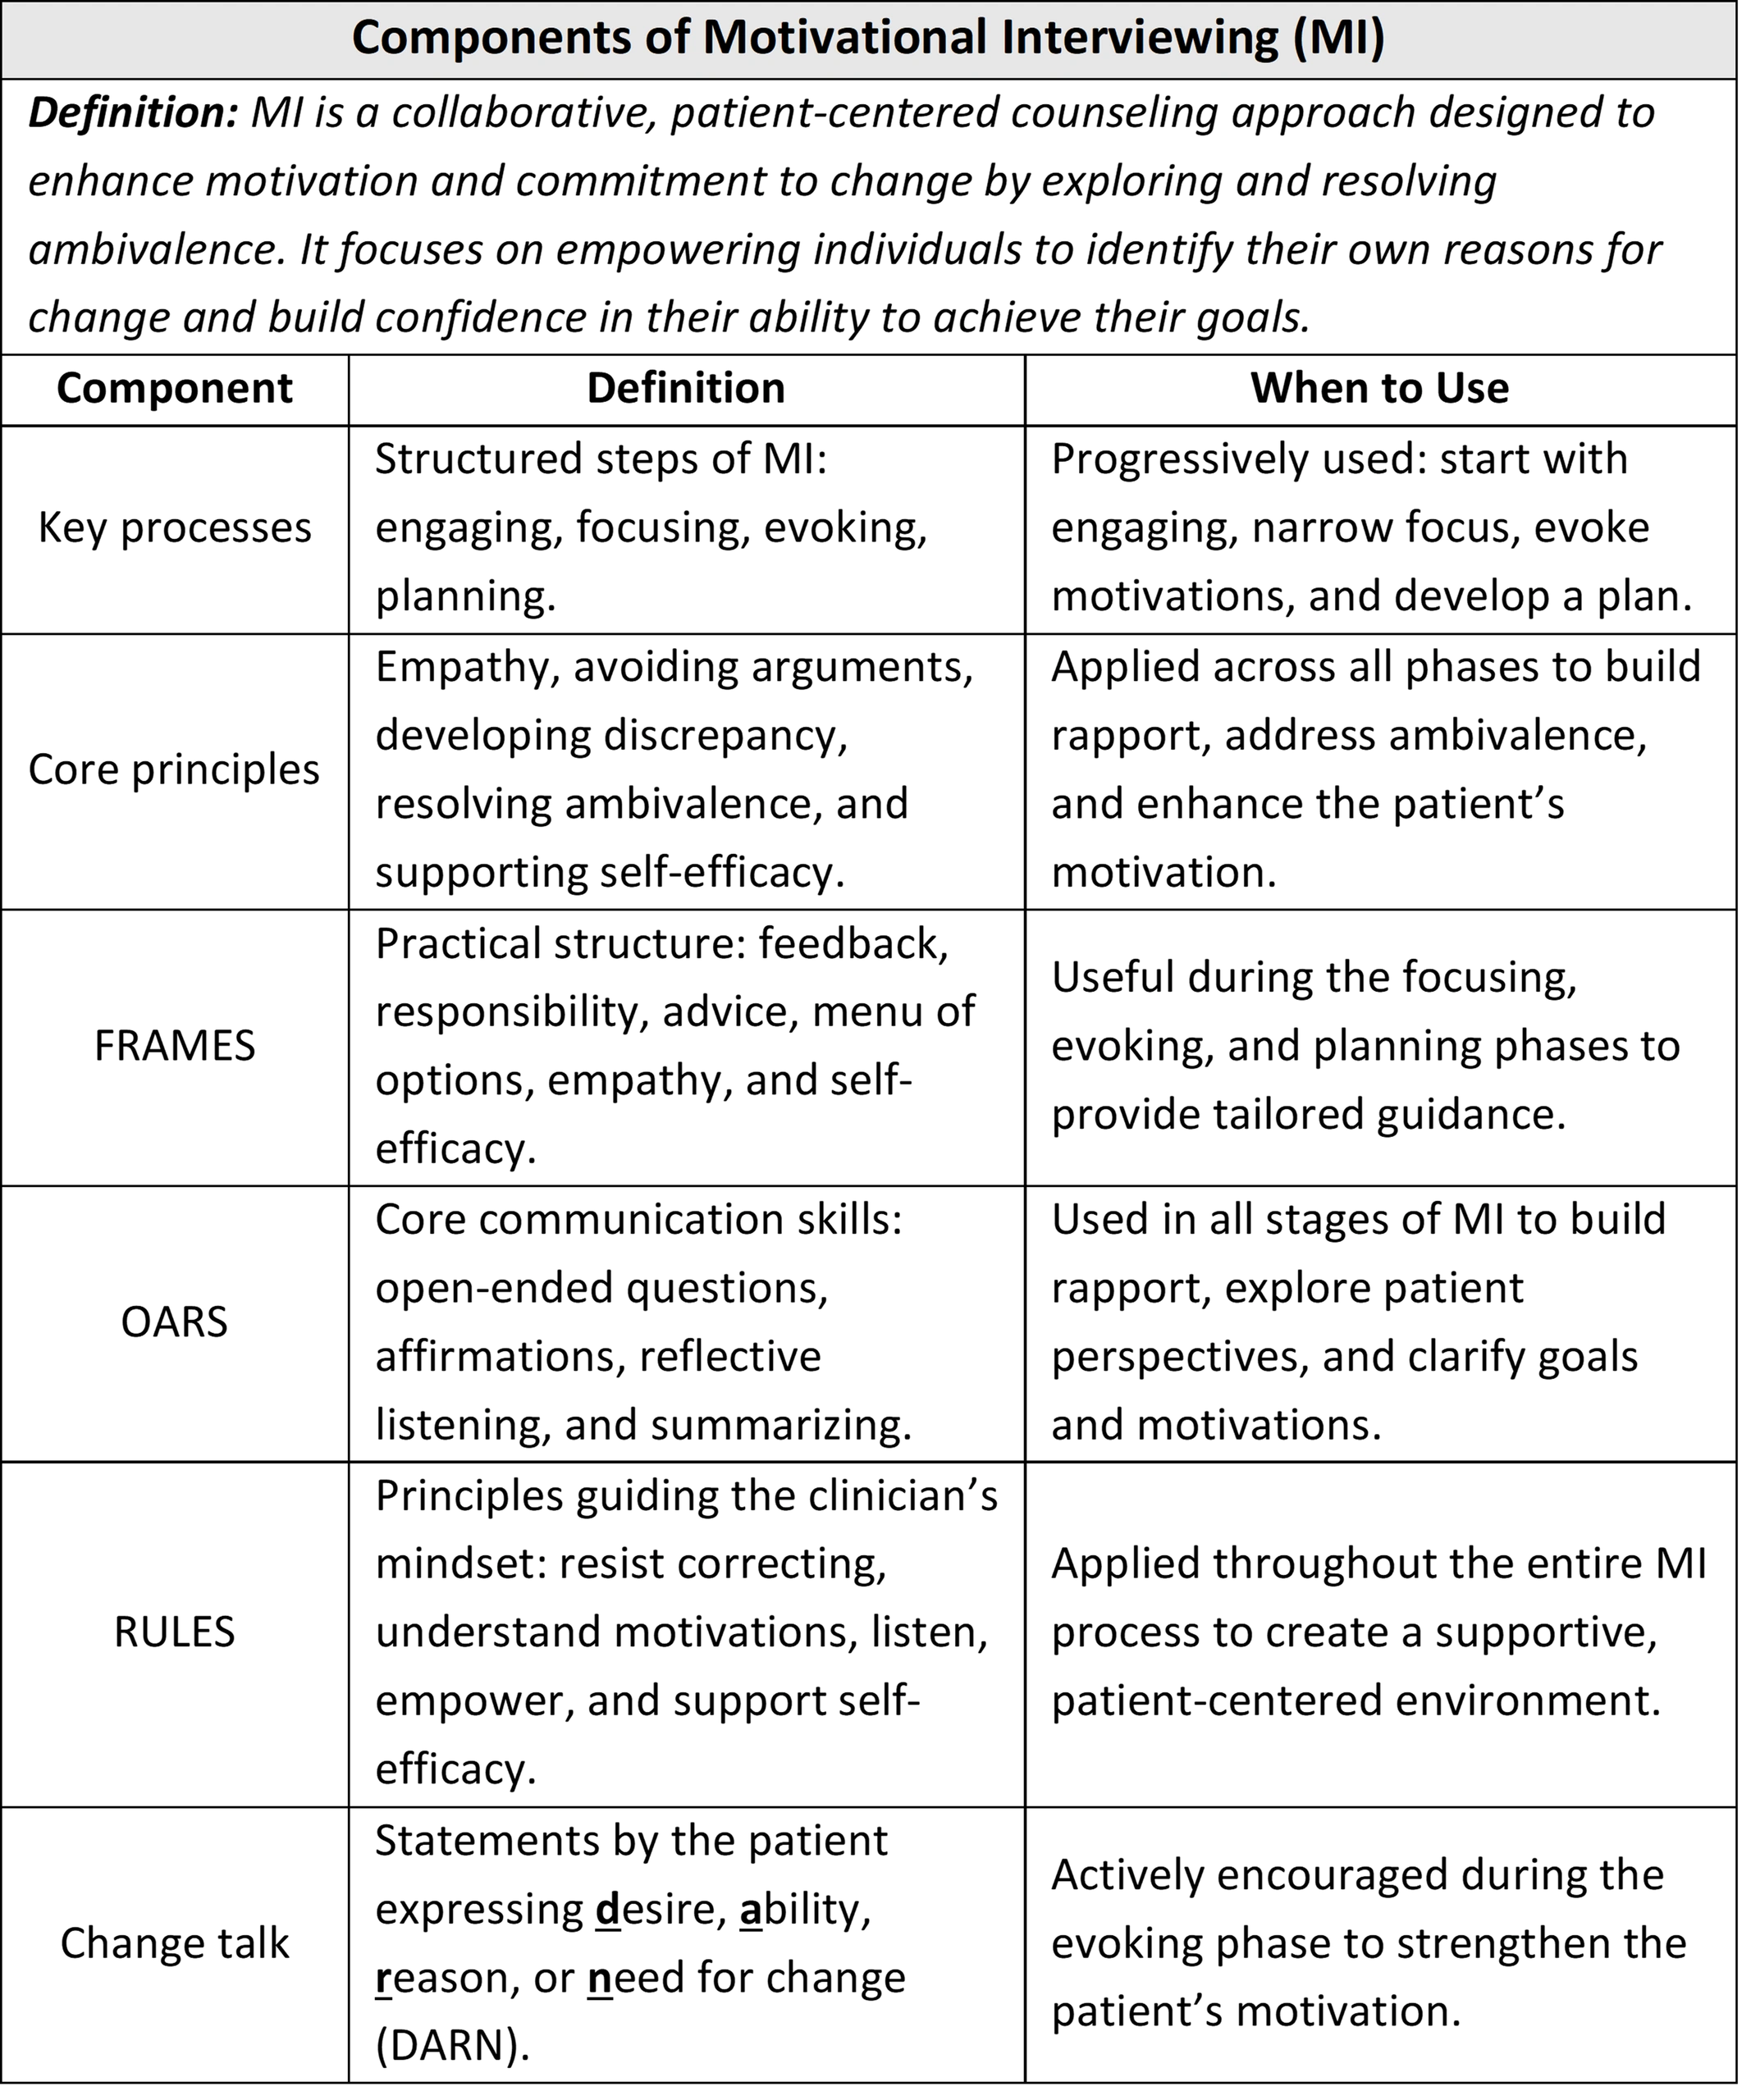
MI consists of numerous components that help move patients through the stages of change from pre-contemplative (unaware that there is a problem) to the action and maintenance stages. Importantly, you are asking questions or providing phrases that promote intrinsic motivation. Simply telling the patient what they should do is not effective, nor the goal. Instead of going through all the components individually, let’s use the above scenario to provide examples of the different MI components:
- 5A’s (Ask): Would it be okay to discuss the recent weight gain before discussing the GLP-1 medications?
- OARS: (O: open-ended question): What do you think contributed to the recent weight gain?
- Four processes of MI (Engaging): Tell me how you have had success with weight loss previously without medications?
- RULES (S: supporting self-efficacy): It sounds like you have achieved success in the past by participating in structured programs. Although it took some additional time, it seemed like you prioritized your health and saw improvements.
- Normalizing: Many patients feel like medications will treat their weight, but are often frustrated when they don’t have the results they would like until underlying behaviors are modified.
- Developing discrepancy: It seems like your primary goal is to lose weight, but you don’t seem as interested in addressing the behaviors that may help you achieve this success.
- FRAMES (M: menu of strategies): Would it be okay if I discussed several strategies that assist with weight loss so we can tackle weight gain from various angles?
These simple examples are just a few that could be incorporated into the office visit. They are not overly time-consuming, but at best, they assist the patient in seeing the importance of how behavioral change, along with medications, may be more effective while building rapport, and at the least, provide the clinician insight into the initial resistance. Whenever you see a patient on the exam that is resistant to change, does not see the value in change, or even if the patient is very motivated but is not connecting the dots between their current behaviors and where they want to be, MI should be an attractive option.
The table below summarizes the different components of MI and where they are effectively used in the different stages of change.
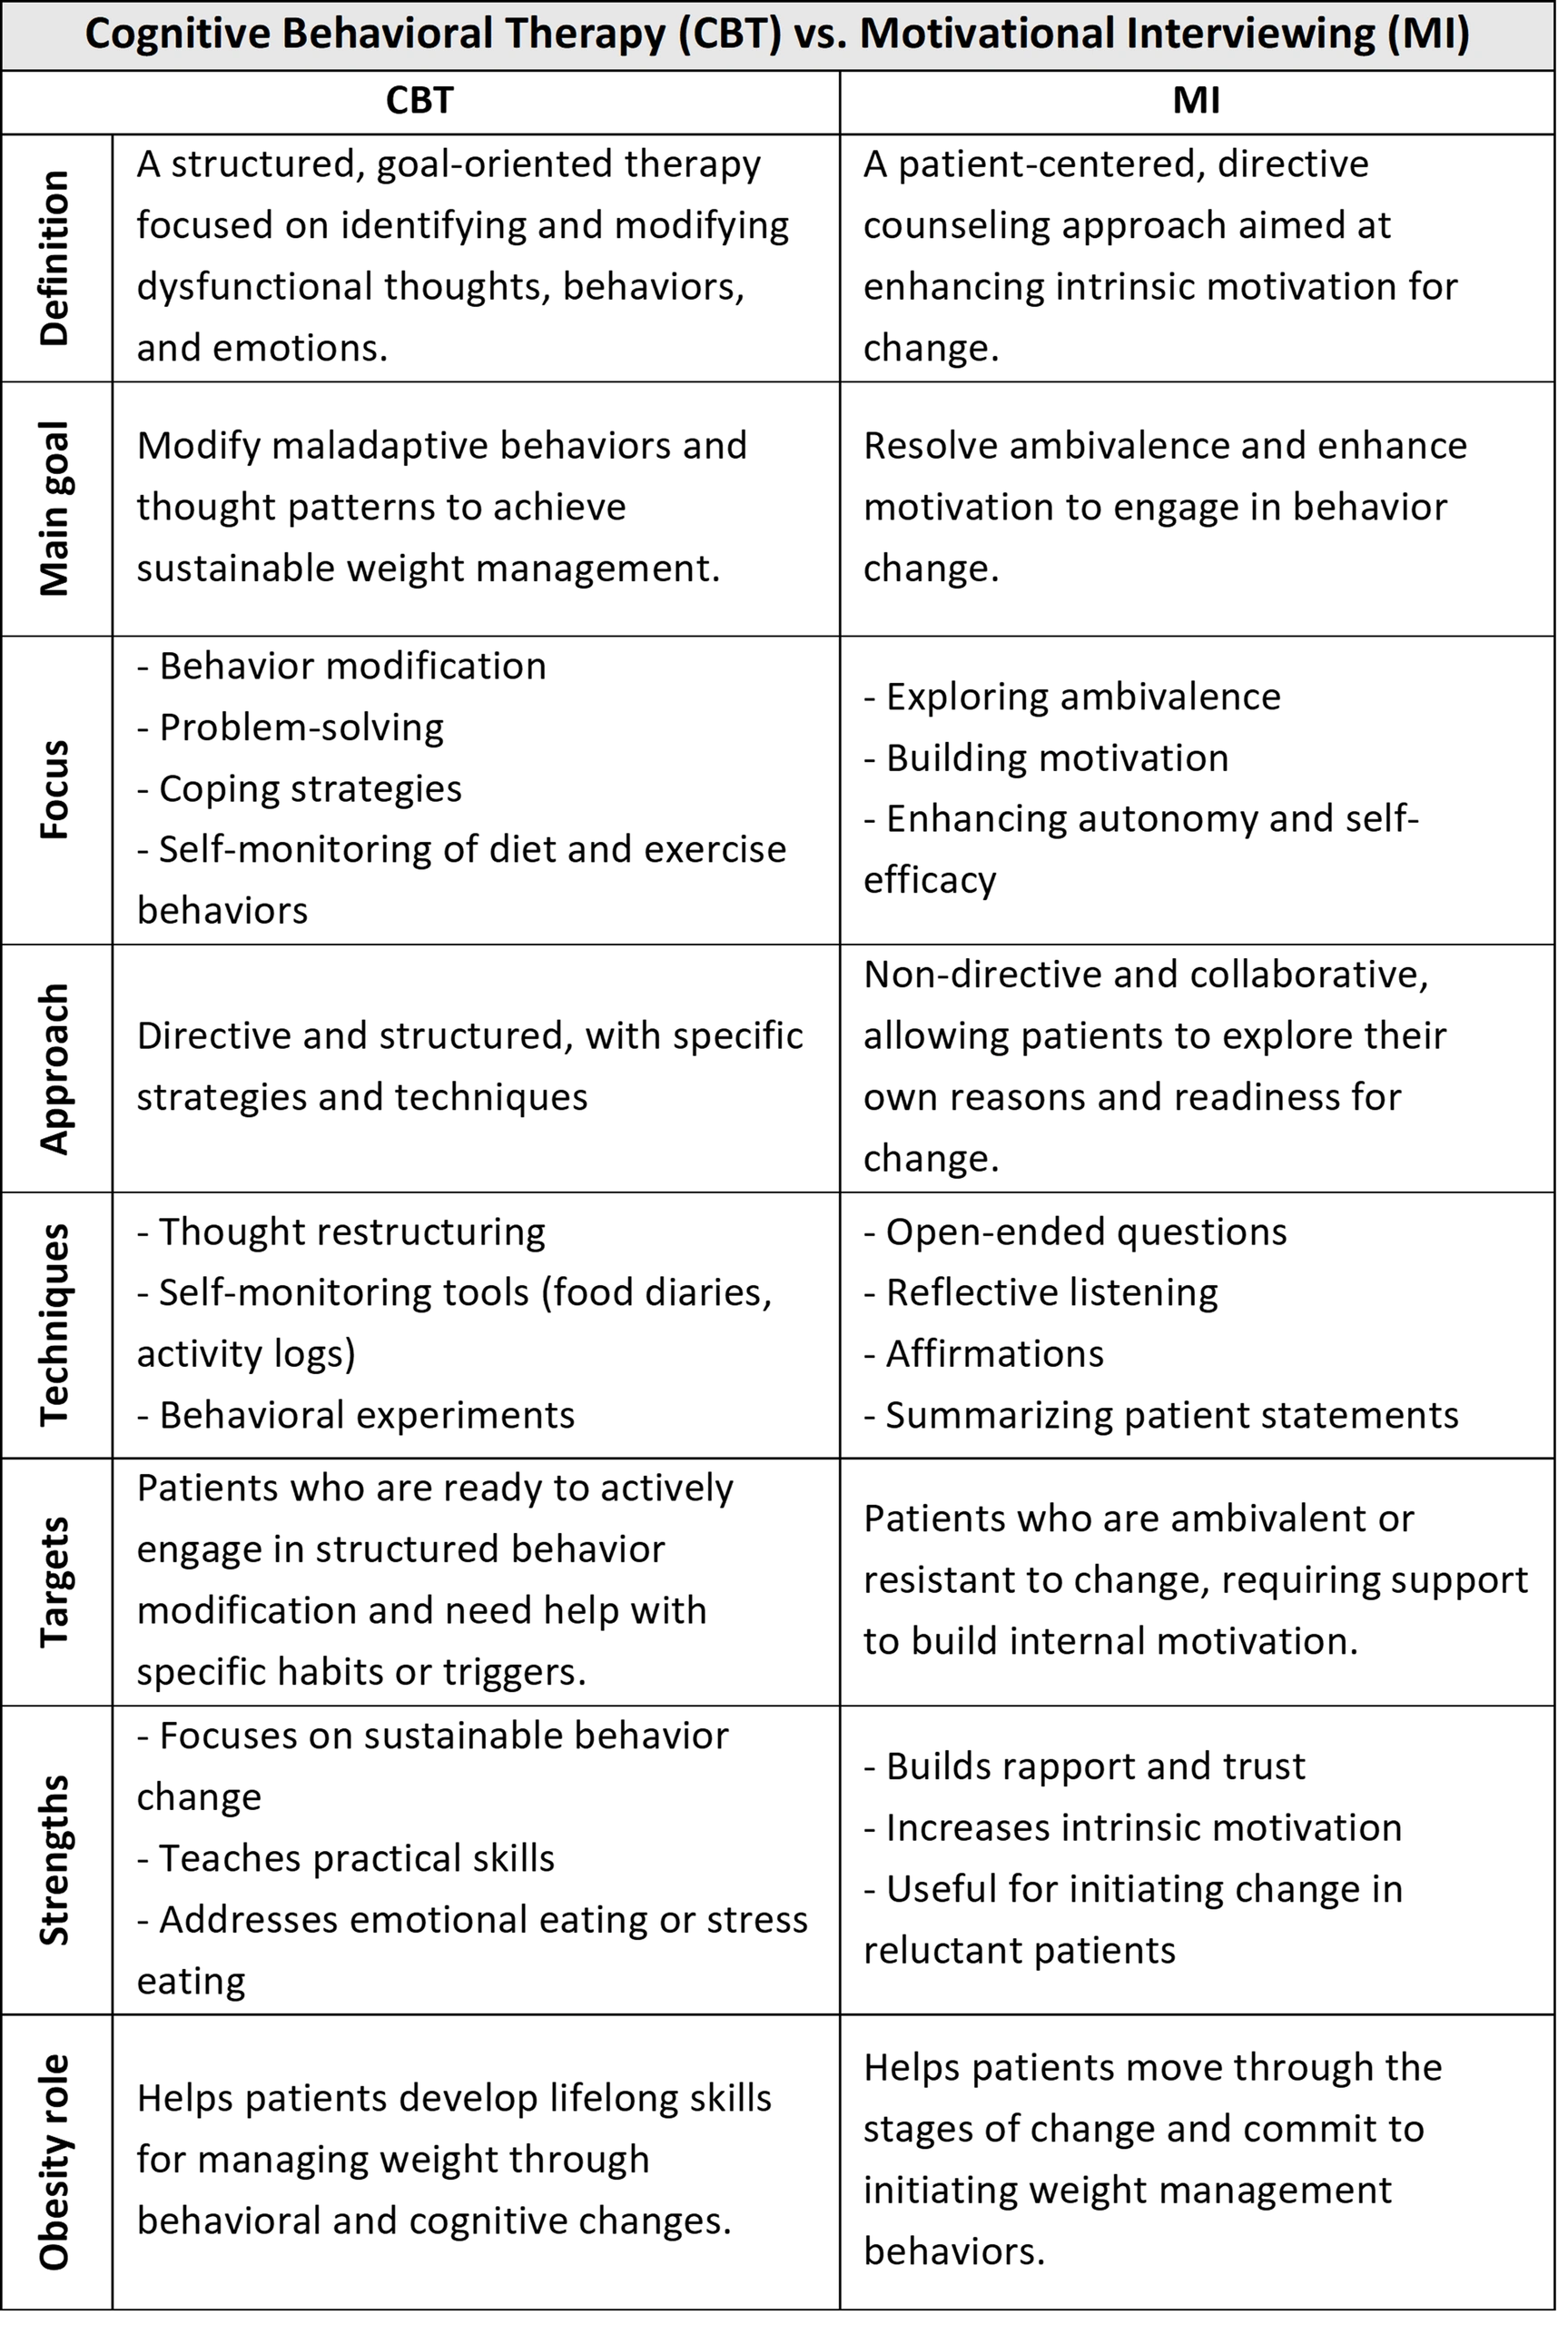
In contrast to MI where you are resolving ambivalence and potentially apathy, CBT includes several strategies that assist the contemplative and motivated patient to succeed. CBT provides the tools and techniques that the patient will utilize to help change behaviors by providing the patient with self-feedback (positive or negative), often via monitoring, thus reinforcing or detracting from certain behaviors. Ultimately, this promotes self-accountability and self-efficacy. The patient is the primary stakeholder in driving the change, taking ownership of the change, and modifying accordingly based on results, while the clinician provides education on how these tools will be employed and provides support through supervised feedback and guidance. There are a wide variety of strategies to employ, with some of the more commonly utilized ones in the table below.

In simplest terms, MI is performed by the physician to help the patient find reasons for change, whereas CBT involves the techniques that the patient will self-employ, monitor, and modify to make those changes. Differentiating between MI and CBT, and understanding the components can be challenging, prompting this blog and additional tables and questions to be added in the question bank to help you master these. I have included one final table that directly compares MI with CBT.
Sample Question
A 28-year-old woman is noted to have episodes of eating significant amounts of food in one sitting and then feeling guilty about it. She denies any purging behaviors and her body mass index is 26 kg/m². She states this has been ongoing for 2-3 years and admits, “This is just who I am.” What is the strongest indication for motivational interviewing in this patient?
A. Guilty feeling
B. Chronicity of symptoms
C. Caloric intake
D. Ambivalence
(Answer and explanation will be provided in an upcoming monthly Knowledge Check.)
Next Week: Vital hormone receptors
Upcoming: Guideline-based care: Reviewing the USPSTF ABOM-recommended resource
Following week: Monthly Knowledge Check. This is a review checklist of must-know items for ABOM exams based on the previous four blog topics (Epitomee, CBT vs MI, vital hormone receptors, USPSTF recs). In addition, this will include a brief explanation of the correct answers to previous sample questions.
For more practice questions, check out the following:

- Obesity Medicine Board Review Questions (2026): Qs 170, 177, and 197.
- Obesity Medicine Practice Tests (2026): Qs 38, 123, 235, 269, 307, 310, 358, 437, and 445.
(Copyright 2026) Obesity Medicine Board Review Questions, LLC: obesitymedicinereview.com
Featured image: Modified from VectorStock (image license purchased)
Copyediting by Kelly Smith

Now available: A full line of ABOM study resources with 775+ challenging questions in a mobile or book format. Access to both formats is available in a discounted Ultimate Package, which also includes a Pass Guarantee (if you fail the exam in 2026, you get the 2027 edition free), 50 bonus questions released in August, and the newest book, Obesity Medicine: Sample Questions and Study Blogs, which includes all the updated previous study blogs in a paperback format. Check it out here!
