

It is impressive that we have numerous hormones secreted throughout the gastrointestinal tract, including CCK, GIP, GLP-1, OXM, and PYY, all aimed at reducing and balancing the one hormone that makes us hungry, ghrelin. This potent orexigenic stimulator of hunger acts via the NPY/AgRP receptors in the brain and, to a lesser extent, via the vagal nerve, to decrease energy expenditure and increase energy consumption.
You may be asking, what is important to know regarding ghrelin? A lot, actually, so bear with me. Ghrelin is fundamental to understanding how patients control appetite and can be a quick win on test day. Make sure you understand and commit the following concepts to memory.
- Production: Ghrelin is mainly produced and secreted by the cells in the gastric fundus and body. It can also be found to a lesser extent in the duodenum. When a patient has a sleeve gastrectomy, 80% of the stomach is removed. Thus, removing 80% of the cells that produce ghrelin. This is why these particular patients rarely complain of hunger.
- Increased levels: Think about what makes us hungry, such as fasting, stress or stress eating, and sleep deprivation including poor quality of sleep such as in the setting of OSA, which can all increase ghrelin levels.
- Suppressed levels: Think of things that can cause a stretched stomach, such as cellulose and citric acid hydrogel or other three-dimensional volume occupying matrixes like Plenity® and Epitomee®, gastroparesis, protein, post-meal, weight gain, vagotomy, and sleeve gastrectomy can all suppress ghrelin levels.
In addition to the hormones secreted in the gastrointestinal tract that counter ghrelin’s effects, leptin is produced by adipocytes, or fat cells. Leptin is a potent nemesis of ghrelin, promoting satiety and inhibiting hunger through opposing effects on the central appetite pathways. Therefore, as fat mass increases, leptin levels generally increase. The opposite occurs with weight loss. As fat mass decreases, leptin levels decrease, while ghrelin levels increase, promoting hunger. Along with reductions in energy expenditure, these hormonal adaptations help explain weight-loss plateaus and the difficulty maintaining weight loss.
Finally, know the common orexigenic and anorexigenic pathways. The diagram below gives a bird’s-eye view of where ghrelin inputs into the central nervous system. Understand that ghrelin has a strong stimulatory effect on the orexigenic or hunger pathway via the first and second-order neurons in the hypothalamus, whereas leptin not only inhibits the orexigenic pathway but stimulates the anorexigenic pathway.
You will need to memorize this entire pathway for boards:
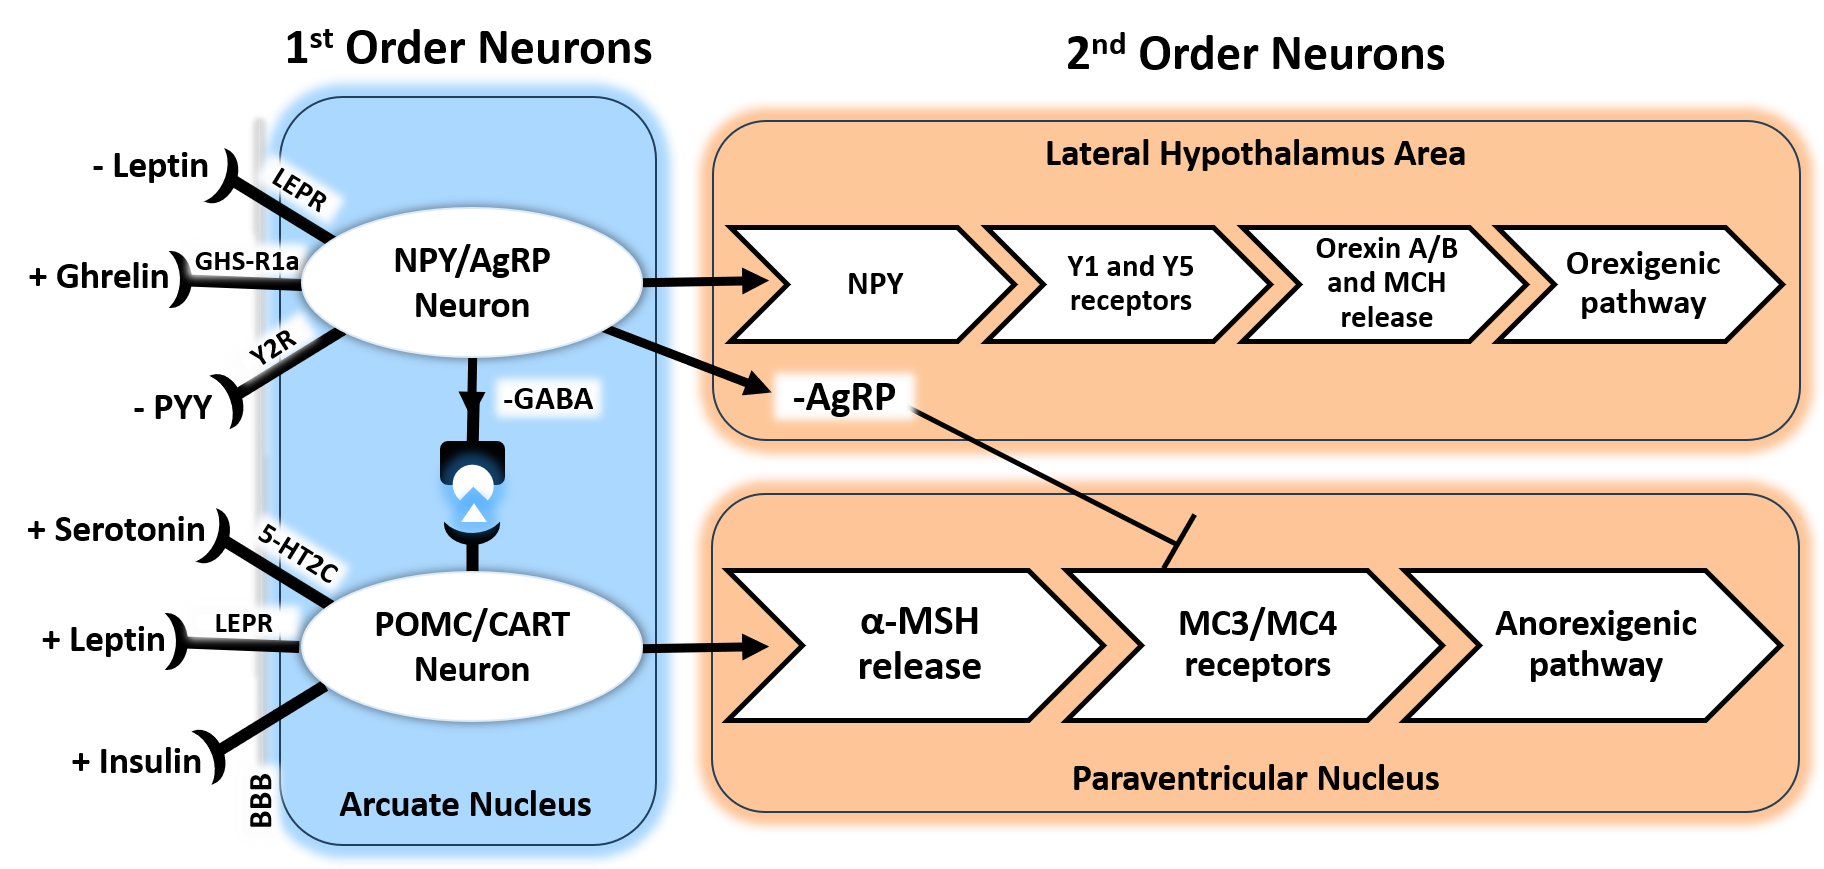
POMC: Proopiomelanocortin; CART: Cocaine and amphetamine-regulated transcript; α-MSH: α melanocyte-stimulating hormone; MC3R/MC4R: Melanocortin 3 and 4 receptors; NPY: Neuropeptide Y; AgRP: Agouti-related peptide; MCH: Melanin-concentrating hormone; PYY: Peptide YY; BBB: Blood brain barrier
Sample Question:
A 33-year-old woman recently underwent a sleeve gastrectomy and is losing weight appropriately. She is most impressed by the decreased appetite she has, irrespective of meals, which has helped in maintaining a significant calorie deficit. The hormone that is responsible for her decreased appetite initially acts on what area of the brain?
A. Dorsal vagal complex
B. Amygdala
C. Nucleus of the tractus solitarius
D. Arcuate nucleus
E. Lateral hypothalamus
Next Week’s Topic: Orlistat
For more practice questions, check out the following:

- Obesity Medicine Board Review Questions (2026): Qs 14, 42, 62, and 71.
- Obesity Medicine Practice Tests (2026): Qs 20, 49, 363, and 431.
(Copyright 2026) Obesity Medicine Board Review Questions, LLC: obesitymedicinereview.com
Featured image: Modified from VectorStock (image license purchased); Orexogenic/Anorexigenic pathway diagram: (© Kevin Smith, DO)
Copyediting by Kelly Smith
Updated: October 3, 2026
