
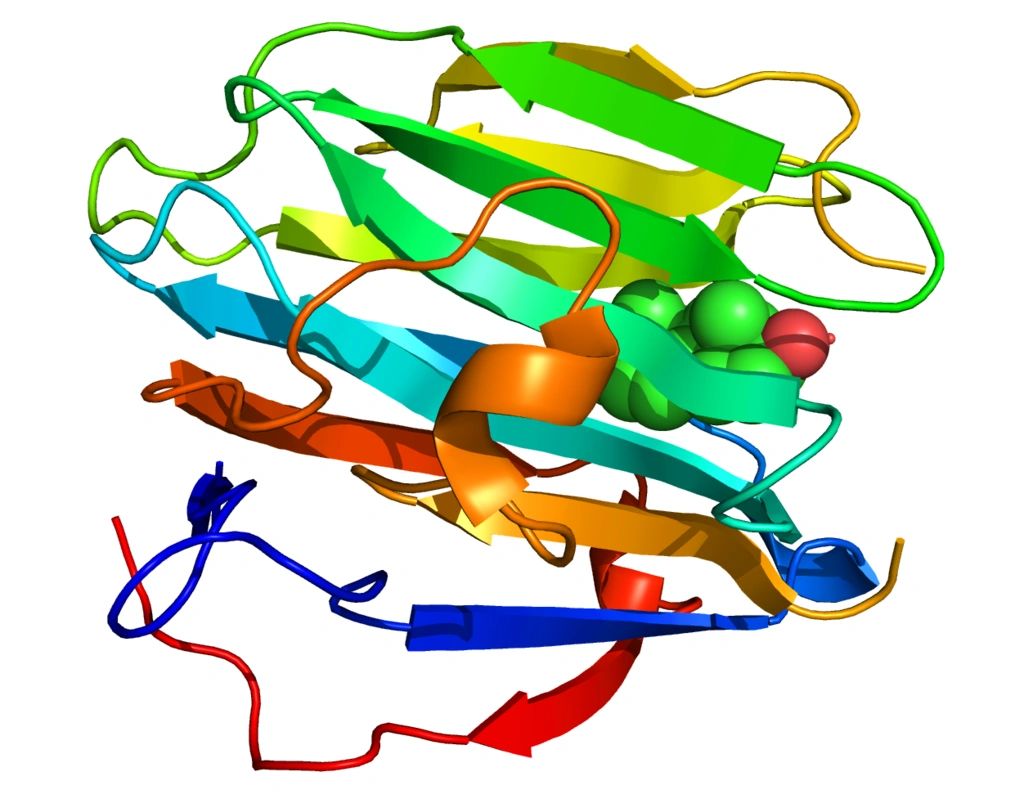
Most of you probably think the title is a misnomer. Why is sex hormone-binding globulin (SHBG) considered a high-yield topic for ABOM boards? If it is important enough to appear multiple times in board review courses, then it is probably important to understand.
So, what is SHBG, and what do you need to know? Know the physiology. If you can understand what it does and what situations affect its levels, you will be golden.
SHBG is a protein made in the liver and, as its name suggests, binds sex hormones, particularly testosterone and estrogen. It carries the hormones throughout the body to where they are needed and when they are needed. Think of this similarly to how albumin binds calcium, or transferrin carries iron. When it is being carried by this protein, it is not able to activate receptors. This is in contrast to free hormones, which can bind to receptors and are considered active. What affects its level? Age, sex, and insulin resistance are the 3 biggest factors that will affect SHBG. On test day, picture a “Little Old Lady” (LOL) to remember who will have the highest SHBG:
- Little: Patients with low BMIs will have higher SHBG. In contrast, patients with obesity will have decreased SHBG. The same is true of insulin resistance, which directly correlates with levels of obesity; patients with increased levels of insulin resistance (think polyendocrine metabolic ovarian syndrome (PMOS), obesity, metabolic syndrome, diabetes, etc.) have decreased SHBG.
- Old: As you age, SHBG will increase. Therefore, younger patients have a relatively lower SHBG level compared to the elderly.
- Lady: Women have higher levels of SHBG. Higher levels of estrogen stimulate SHBG production in the liver. Therefore, in women, especially during pregnancy and those on estrogen hormone replacement therapy, SHBG production is increased.
Finally, remember that SHBG binds testosterone, and bound testosterone is not active. In other words, higher levels of SHBG equate to lower circulating levels of free (i.e., active) testosterone because it is bound to SHBG. A great example of this is in patients with PMOS. They have lower SHBG = higher free testosterone levels = increased androgen effects.
Don’t be caught off-guard. Understand these concepts regarding SHBG (to this degree) and you will be able to reason your way through any of these related questions on test day
Sample question:
A 26-year-old woman presents for a gynecologic evaluation after being evaluated in the emergency department for pelvic pain. A pregnancy test was negative and an ultrasound revealed multiple bilateral ovarian cysts. Which of the following would most likely be decreased in this patient?
A. Sex hormone-binding globulin
B. Luteinizing: follicular-stimulating hormone ratio
C. Free androgens
D. Prolactin
Next Weeks Topic: Ghrelin
For more practice questions, check out the following:

- Obesity Medicine Board Review Questions (2026): Qs 93, 147, and 154.
- Obesity Medicine Practice Tests (2026): Qs 90, 140, 230, and 298.
(Copyright 2026) Obesity Medicine Board Review Questions, LLC: obesitymedicinereview.com
Featured image: (2020, May 13). Wikimedia Commons, the free media repository.
Copyediting by Kelly Smith
