

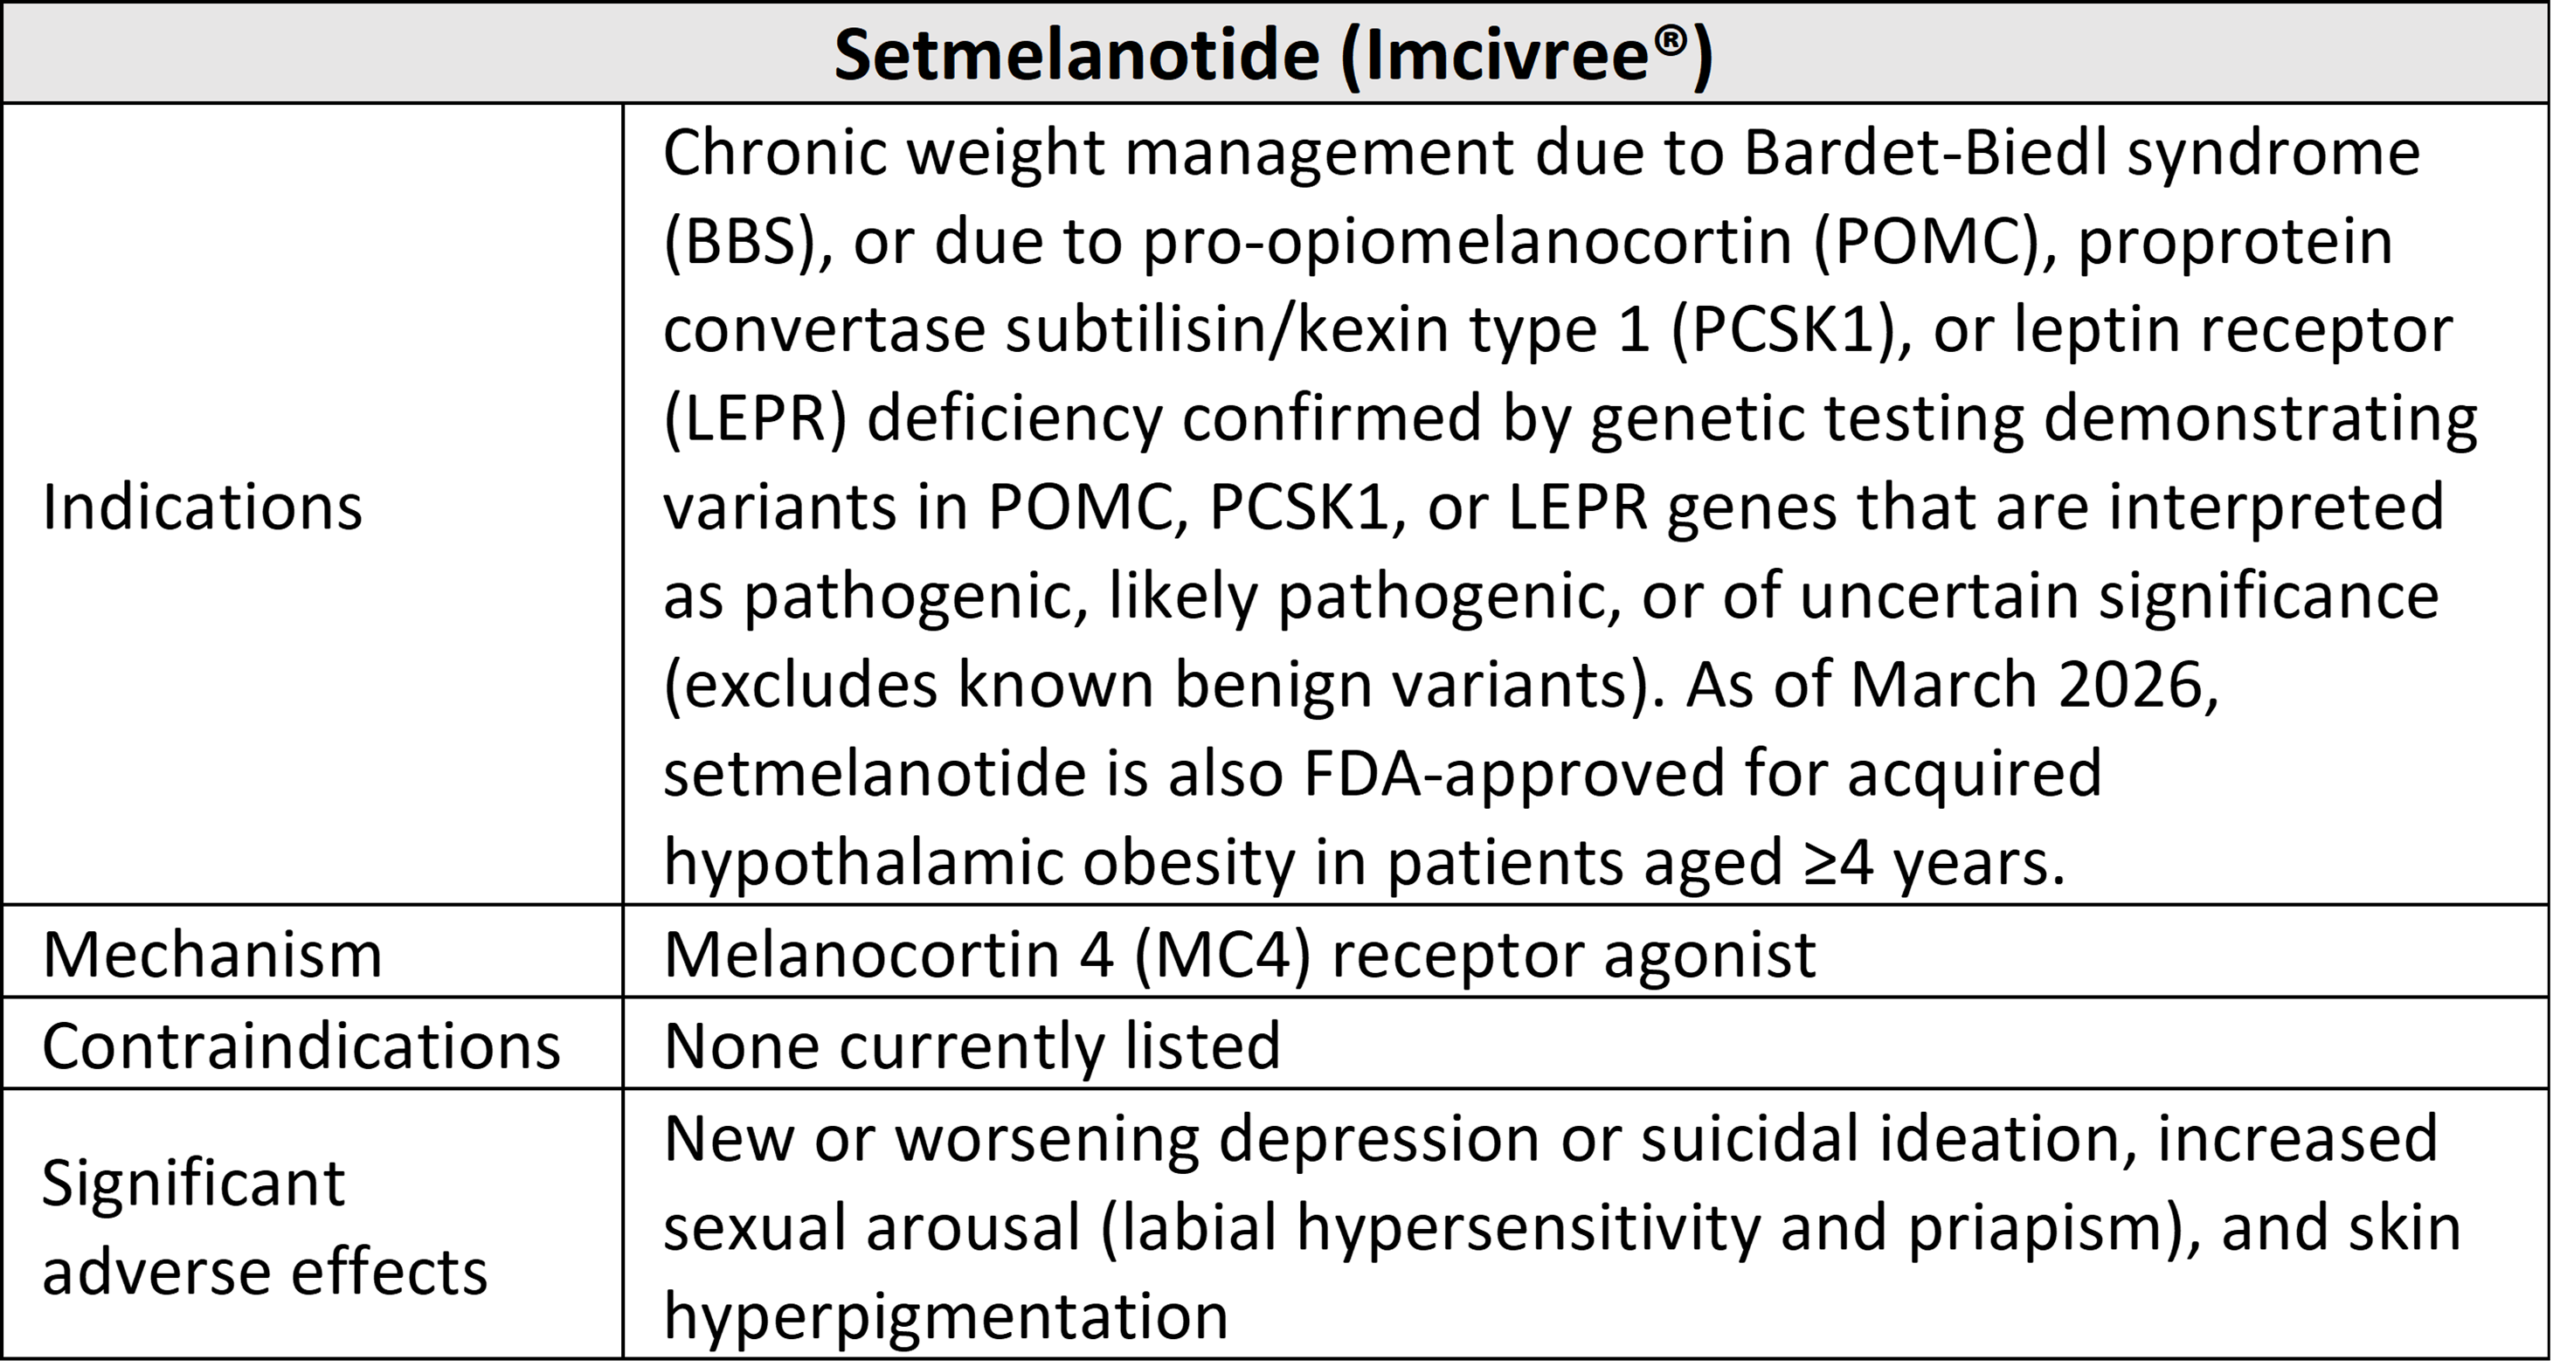
Setmelanotide (Imcivree ®) is one of the costliest medications to treat obesity. This is a melanocortin 4 receptor (MC4R) agonist indicated for the treatment of certain genetic etiologies of obesity, including Bardet-Biedl syndrome as of 2022, as well as acquired hypothalamic obesity as of 2026. Deficiencies or pathogenic variants of pro-opiomelanocortin (POMC), proprotein convertase subtilisin/kexin type 1 (PCSK1), or leptin receptors (LEPR) are also indications.
Note: Metreleptin, a leptin replacement, is approved for congenital leptin deficiency with lipodystrophy, not leptin receptor deficiency. If the leptin receptor is deficient or defective, providing a leptin analog such as metreleptin will not have any downstream effects. Similarly, a patient with MC4R deficiency would not benefit from setmelanotide because if the receptor is broken or deficient, providing more analogs cannot activate the receptor.
Recall from a prior blog that the central anorexigenic pathway has MC4 receptors as one of the most distal receptors in the hypothalamus. By examining the pathway below, if there are any receptor mutations proximal to this (POMC, leptin, etc.), the MC4 receptors will not be activated, and thus the anorexigenic effect will not be fully stimulated. As expected, this leaves the orexigenic (weight-gaining) pathway unopposed, leading to insatiable hunger and early-onset obesity. By activating the distal MC4 receptor with setmelanotide, an MC4 receptor analog, you bypass any proximal receptor mutations or deficiencies and can still activate the anorexigenic pathway.
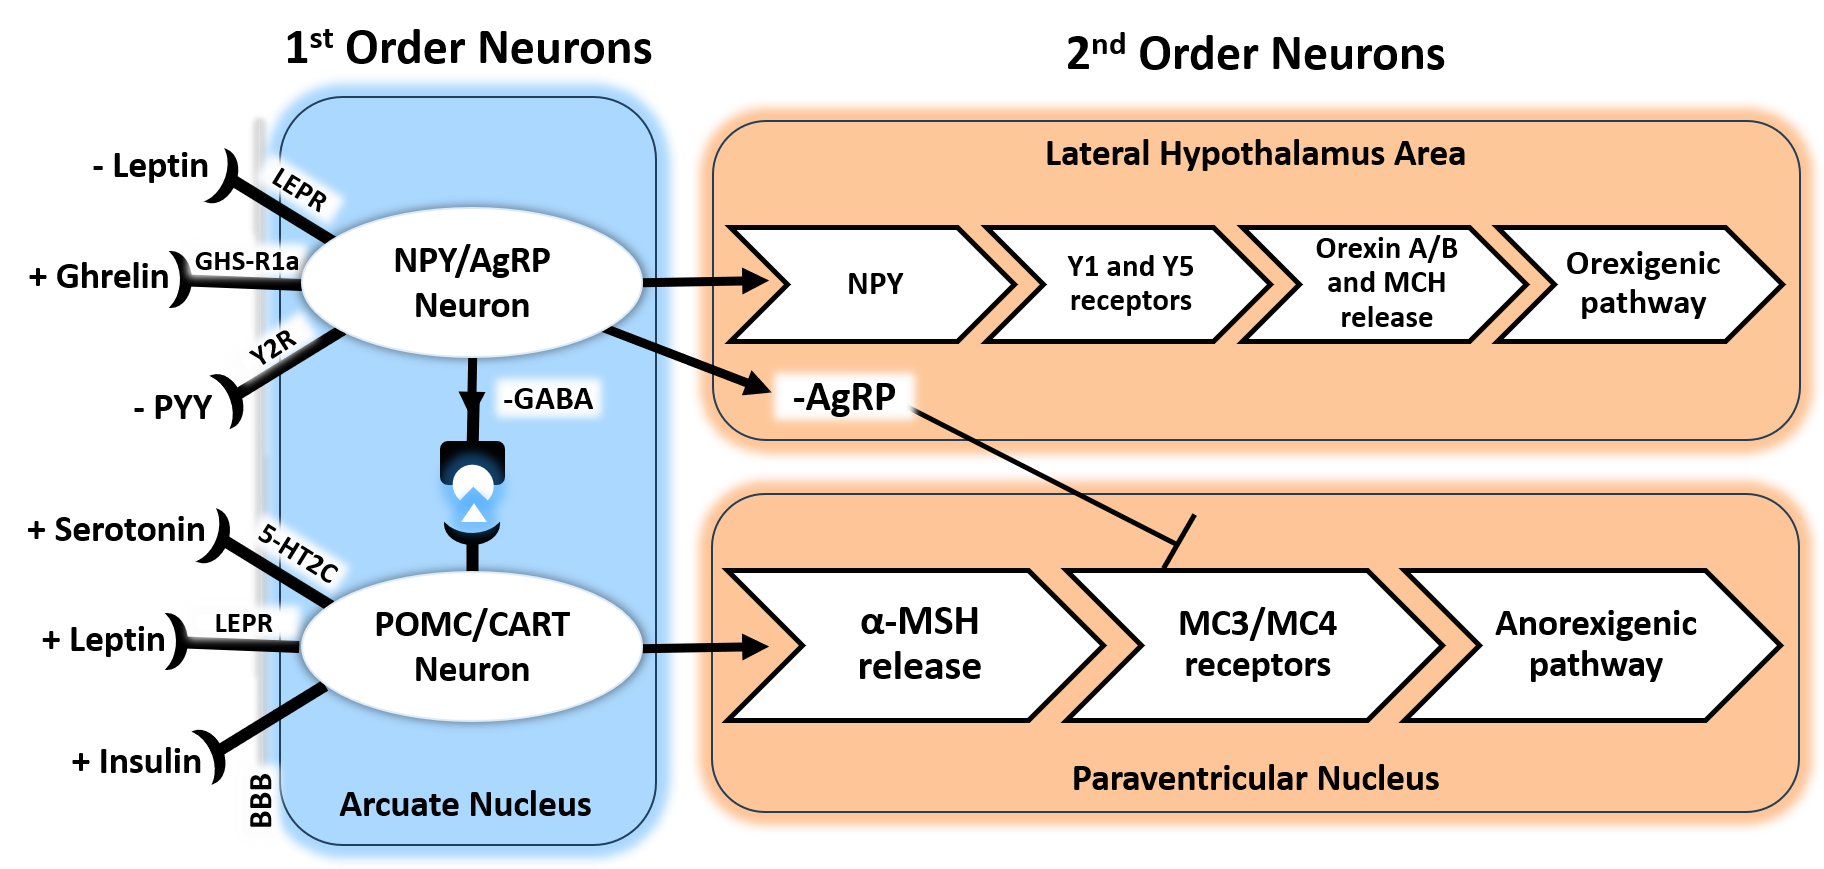
POMC: Proopiomelanocortin; CART: Cocaine and amphetamine-regulated transcript; α-MSH: α melanocyte-stimulating hormone; MC3R/MC4R: Melanocortin 3 and 4 receptors; NPY: Neuropeptide Y; AgRP: Agouti-related peptide; MCH: Melanin-concentrating hormone; PYY: Peptide YY; BBB: Blood brain barrier
Testing for genetic abnormalities leading to obesity is indicated in early-onset obesity, defined as obesity occurring before 5 years of age or with early-onset hyperphagia. It makes sense that these variants have to be genetically confirmed (provided for free by Rhythm® Pharmaceuticals) in order to treat with setmelanotide, given the price tag of $25k per month. In other words, you could buy nearly 3 years’ worth of semaglutide or pay cash for metabolic and bariatric surgery for the same cost as one month of setmelanotide.
The conditions approved for setmelanotide, along with some unique characteristics, are summarized below:
- Proopiomelanocortin gene mutations lead to an adrenal crisis in neonates due to ACTH deficiency, which is produced from POMC (hypothalamus) as well as alpha-melanocyte-stimulating hormone, which is involved in reducing food intake. These patients tend to have pale skin and red hair due to decreased melanocyte stimulation.
- LEPR deficiency: Patients with leptin receptor gene defects have difficulty suppressing their appetites. They also experience insulin resistance but do not have tall stature (as is seen in MC4R deficiency) and may have frequent infections, as one leptin subtype is involved in the immune system.
- PCSK1 deficiency: PCSK1 gene encodes a proprotein convertase involved in processing multiple peptide hormones that regulate hunger, satiety, and energy homeostasis. PCSK1 deficiency can cause severe diarrhea and malabsorption beginning in infancy, followed by hyperphagia and early-onset obesity. Patients may also develop various endocrinopathies, including diabetes, growth hormone deficiency, and hypothyroidism.
- Bardet-Biedl syndrome was discussed thoroughly in a prior blog (click here.)
- Hypothalamic obesity: Damage to the hypothalamus, most commonly from tumors such as craniopharyngiomas or their treatment (surgery or radiation), but also from traumatic brain injury, can disrupt central pathways regulating hunger, satiety, and energy expenditure, resulting in rapid and often severe weight gain.
Besides knowing the indications for this medication, some unique side effects may occur with this medication. In particular, significant adverse reactions associated with setmelanotide include new or worsening depression or suicidal ideation, increased sexual arousal (labial hypersensitivity and priapism), and skin hyperpigmentation. The latter effect is common because, in addition to its effects on the MC4R pathways associated with anorexic effects, setmelanotide may also stimulate MC1R skin receptors, which regulate skin pigmentation
Sample Question
An 8-year-old girl is diagnosed with Bardet-Biedl syndrome, and a discussion of treatment options ensues. Which of the following is a potential side effect of the FDA-indicated therapy?
A. Nephrolithiasis
B. Tachycardia
C. Gastroparesis
D. Skin hyperpigmentation
Next Week: VO2 max
Upcoming: Monthly Knowledge Check. This is a review checklist of must-know items for ABOM exams based on the previous four blog topics (Hypothalamic obesity, gastric balloons, setmelanotide, and VO2 max). In addition, this will include a brief explanation of the correct answers to previous sample questions.
For more practice questions, check out the following:

- Obesity Medicine Board Review Questions (2026): Q 273.
- Obesity Medicine Practice Tests (2026): Qs 187, 199, 274, 288, and 304.
(Copyright 2026) Obesity Medicine Board Review Questions, LLC: obesitymedicinereview.com
Featured image: Modified from VectorStock (image license purchased)
Copyediting by Kelly Smith
